
CPT Code Lookup for Billing Teams: Descriptions, Fees, and Clean Claims
Your billers look up CPT codes all day, and most of the time it feels like a quick job: type a description, …

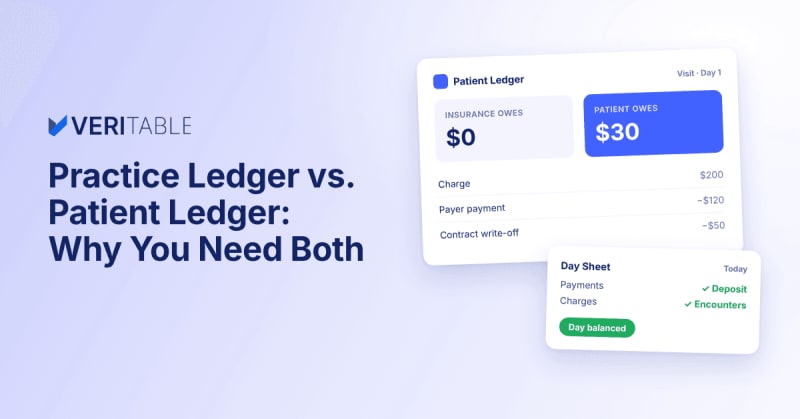
Suppose you close the day sheet and it balances. Then you open a patient’s account and see a $30 balance that became theirs today, with no $30 debit or credit on that sheet. Both are correct.
If you treat the two ledgers as the same money seen twice, this looks like an error. You lose time hunting a mistake that isn’t there, and the patient still has no explanation.
The practice ledger, or day sheet, shows what moved in the practice today. The patient ledger shows where one account stands, and why. They differ because they answer different questions.
This article will cover:
Before billing software, medical offices often wrote both ledgers in one handwritten entry, on a pegboard. A pegboard was a manual bookkeeping board: pegs held the practice’s day sheet and a patient’s ledger card lined up, and carbon or carbonless paper carried one write-up onto both at once.
The pegboard still appears in training material. Exam prep material for certified medical assistants introduces the day sheet as historically the pegboard or “write-it-once” system, and medical office textbooks carried “pegboard” in their titles into the 2010s.
Software replaced the paper but kept both outputs. You may never have seen a pegboard. The two screens in your billing software descend from it all the same.
What is a patient ledger? A patient ledger follows one account, organized by date of service and claim, so a biller can explain every dollar the patient owes. The date of service is the date of the visit.
The screen shows two balances, not one: what insurance owes and what the patient owes. Billing systems commonly show the two side by side, kept separate.
Each balance also has an age. Aging is how long a balance has been outstanding, sorted into buckets of 0-30, 31-60, 61-90, 91-120, and 120+ days. On a patient balance, the clock commonly starts on the date the balance became the patient’s responsibility, not the date of service.
Your aging report may start the clock at the date of service instead. Systems differ: some let you age from either date, and others always age from the date the balance became the patient’s. Check which one yours uses.
The choice moves balances between buckets. A visit from 40 days ago whose balance became the patient’s 20 days ago is in the 31-60 bucket under one rule and the 0-30 bucket under the other.
Patient ledgers often include an on-account bucket too. That is patient money received but not yet applied to a charge, such as a prepayment.
Instead of one page per day, the patient ledger lists only the dates with activity. Most days, a single account has no activity. The list usually covers a lookback window, such as the last 12 months.

The day sheet is a dated journal of debits and credits. The patient ledger is a running account with two balances and a marker for who owes each one.
The marker is the responsible party: the field that says who owns each open balance, whether the primary payer, a secondary payer, or the patient. It changes over a claim’s life, because money moves between payer and patient as the claim gets paid.
Debits and credits are enough to run the day sheet, but not the patient ledger. And the patient ledger cannot show what posted across the practice on a given day. That is why billing software keeps both.
We invented the visit below to show the mechanics. It is a $200 charge, paid partly by insurance and partly by the patient.
| Event | Day sheet | Patient ledger |
|---|---|---|
| Day 1: the visit is charged | $200 debit on the day-1 sheet | Under the day-1 visit: insurance owes $200 |
| Day 21: the payer pays $120, $50 is written off under the payer’s contract, and $30 is left for the patient | Two credits totaling $170 on the day-21 sheet, among every other patient’s postings that day | The same two credits, filed under the day-1 visit. Insurance owes $0 and the patient owes $30. The responsible party changes to the patient, and the aging clock starts |
| Day 40: the patient pays $30 | $30 credit on the day-40 sheet | Patient owes $0 |
Day 21 shows what each ledger cannot do.
First, the $30 moving from insurance to the patient changes no debit or credit total on the day sheet, because no money moved. On the patient ledger it is the most important event in the claim. The day sheet’s debits and credits cannot say who owes that $30.
That is how a $30 patient balance can appear on a day whose sheet balanced with no $30 debit or credit on it.
Some systems list the move separately, in a transfers view of the day sheet report that shows balances moved to the patient or to a secondary payer, kept apart from the debits and credits.
Second, the same payment is recorded in two places. The day sheet files the $120 under day 21, the day it posted. The patient ledger files it under the day-1 visit and the claim it paid.
So the patient ledger cannot show you everything that posted on day 21, and a patient’s balance and the day sheet do not line up one-to-one.
A single net balance would look simpler. It would also hide the one thing you need before sending a bill. The patient should be billed only for their part, and the insurance part is a follow-up job with the payer. One net number cannot tell you which is which.
None of this means the ledgers disagree. This visit’s day-sheet lines through day 21 add up to $200 in debits and $170 in credits, so $30 is still owed: the same $30 the patient ledger shows.

A guarantor is the person who pays, and a guarantor ledger groups every patient that person is financially responsible for into one balance. A parent who covers their own care and two children’s, for example, has one guarantor ledger spanning three patients.
Each family member still keeps their own patient ledger, with their own visits, claims, and balances. The guarantor ledger adds them up, so the family’s total is in one place.
Some electronic remittances, the payer’s explanations of payment, report a payment only for the whole claim. There is no line detail tying each dollar to a specific charge. When that is all the payer sent, the accurate way to post it is at the claim level.
Claim-level reporting can be legitimate. The electronic remittance standard requires line detail for professional claims and for adjustments tied to a specific line. Elsewhere, claim-level reporting alone can be correct under the standard, as with an outpatient facility case-rate payment, one flat amount for the whole case.
Posting to the claim keeps the ledger balanced without splitting the money across procedure codes yourself, which would invent numbers the payer never sent. Some systems do it automatically. Others send it to a person to post by hand.
A claim-level reversal of a payment first reported line by line is a different problem: a payer formatting error.
Join over 3,200 subscribers and keep up-to-date with the latest innovations & best practices in Healthcare IT.
Your billers look up CPT codes all day, and most of the time it feels like a quick job: type a description, …

Monday morning. Your schedule is full, two new patients still show "unknown" coverage, and someone on the team …

A billing manager at a six-provider practice has forty self-pay accounts sitting in a worklist this month. …
No pricing page to dig through. No demo call to sit through first. Just what you'd actually pay, sent straight to your inbox.
One email. Zero spam.